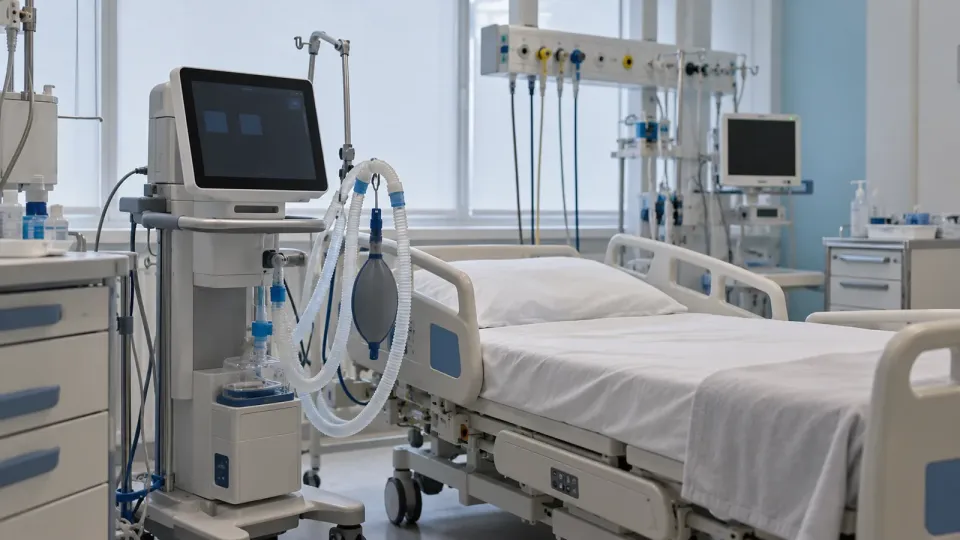
A ventilator takes over a patient's breathing in full or in part when the patient cannot breathe alone or breathes too little. Mechanical ventilation is needed in intensive care and in the operating room. Neonatal ICUs rely on it too, as do teams transferring a critical patient. The Finer catalog lists ventilators by Siare, Fanem, Chenwei Medical plus GINEVRI. It covers ICU and transport models, neonatal ventilators, manual resuscitators as well as several related devices.
How does a ventilator work?
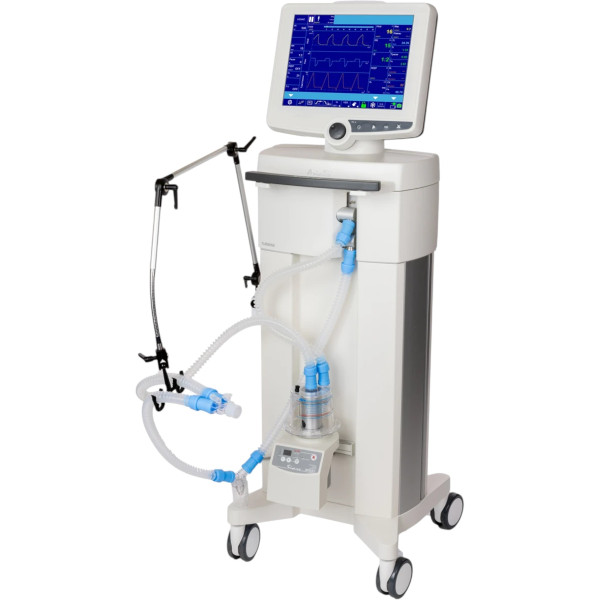
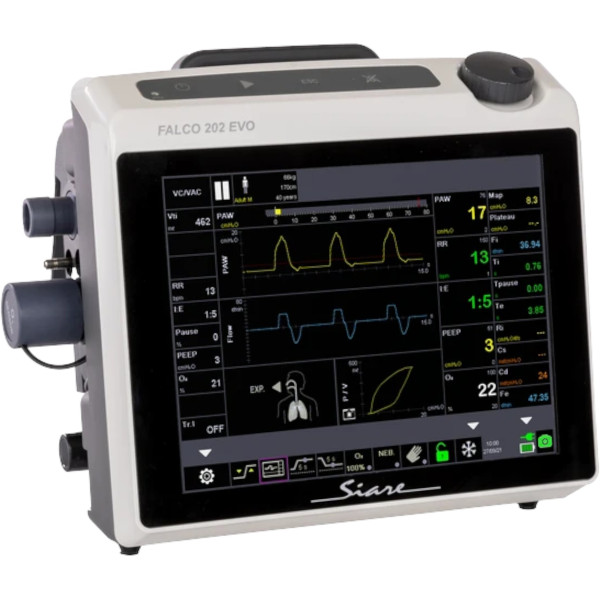
The machine delivers a gas mixture into the lungs at a set volume or pressure. It holds the breath rate, oxygen concentration (FiO2) as well as end-expiratory pressure (PEEP), while its sensors measure every breath. The screen shows curves of pressure, flow or volume over time, so the doctor sees how the patient responds to the settings.
Invasive ventilation goes through an endotracheal tube or a tracheostomy. Non-invasive ventilation (NIV, CPAP) uses a mask or nasal cannulas, so leak compensation matters: on the FALCO 202 EVO TRANSPORT it reaches 60 L/min. An ICU ventilator supports both methods. A transport unit sticks to a basic set. In the operating room the same job is usually done by an anesthesia machine with a built-in ventilator.
How do you choose a ventilator for a department?
Start with the patients. A neonatal model needs small tidal volumes and a precise trigger, while an adult needs a different scale. A universal machine lets several departments run one type, though neonatologists usually ask for a separate device for premature babies. The second question is gas. A model with a built-in turbine draws room air and works without a central compressed air supply, needing only oxygen from the wall. A pneumatic ventilator needs both gas lines or cylinders, but it is simpler and lighter. Draw up the mode list with your doctors: volume control, pressure control, SIMV, pressure support, CPAP. Dozens of rare modes in a specification raise the price, and few people ever switch them on.
Weight and battery life decide for transfers. Our product cards list battery operation of up to 6, 10 or 14 hours. If a ventilator does not measure EtCO2 itself, a separate capnograph is added. Touchscreens of 10.4″ and 15″ are convenient in intensive care, while simple transport units and manual devices keep a pressure gauge. When intensive care uses the same line of ventilators as the transport team or the emergency department, staff move between them more easily.
Which ventilators are in the Finer catalog?
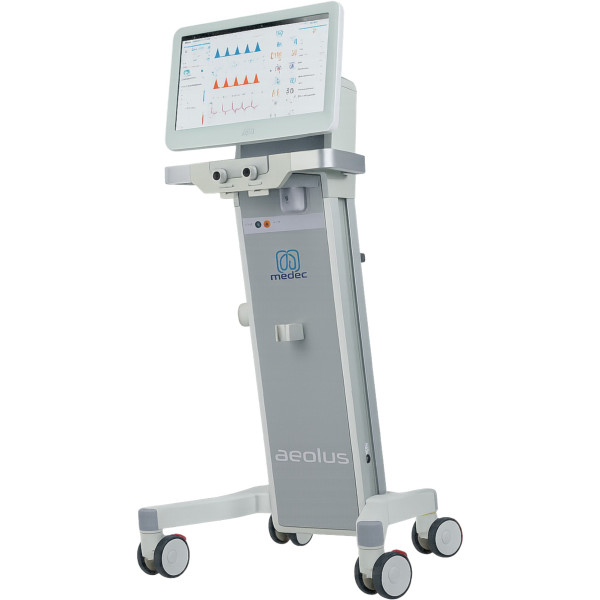
For intensive care there is the Servo-i® ICU ventilator, which works with adults and children as well as newborns. SIARETRON 4000 is positioned as a high-power unit with a 15″ display, and ARIA 150 is built for intensive care. T80 and CWH-3010A use a turbine flow generator, while Aeolus with microprocessor control suits adults and children. The FALCO 202 EVO ventilator covers patients of every age including infants. Its FALCO 202 EVO TRANSPORT version comes in a shock-resistant housing.
The portable SIRIO S2/T ventilator weighs 3.7 kg. OXIVENT is portable too. The CWH-2010 card describes it as a respirator for field and emergency use, and PG VENT for emergency care has an 18.3″ touchscreen. Neonatologists can choose the Giulia neonatal ventilator, SIRIO BABY 200 or the pneumatic Baby Start for delivery rooms. There is also the Babypuff 1020 manual ventilator plus the Bubble CPAP FOG 2140 and 2140A humidifiers. The RICAP capnograph monitors CO2 in exhaled air, and CAP 700 is a cough assist device. Transport models have a page of their own: Portable and transport ventilators.
What does the price of a ventilator depend on?
Some models are priced on the site, and for the rest we prepare a quote on request. The price of one and the same model shifts a lot with its configuration. The mode package matters, as do the neonatal option, the capnography module, a humidifier, a trolley or vehicle mount and spare circuits. For an accurate quote, tell us which department the ventilator is for and which patients will be ventilated. Add the gas supply the hospital has and whether there will be transfers. The quote will then include only what the department will actually use.
Where to buy a ventilator?
ICUs and operating theatres, along with medical transport services, have been getting equipment from global manufacturers through Finer Ukraine LLC since 2015. Before pricing a quote, our team's doctors and engineers go over the patient profile with the head of department, along with the gas supply and transfer routes. Then they prepare the tender documents, deliver the ventilator, start it up on the ward and train the staff. For an ICU or a whole new department there are turnkey solutions. Defibrillators usually stand next to the ventilators, and other equipment is in the Medical Equipment section. If you are ready to buy a ventilator, ring 0 800 334 585 or leave a request in the form on the contacts page.
FAQ
1. When is a ventilator needed?
When a patient does not breathe alone or breathing does not provide enough gas exchange. Typical cases are general anesthesia or severe respiratory failure in intensive care. Premature babies may need it, as may a critical patient during transfer. The doctor decides on ventilation and its mode, and the machine carries out the settings.
2. What does a ventilator show on its screen?
The set and measured values: tidal volume, rate, airway pressure, PEEP plus FiO2, along with curves of pressure, flow or volume. EtCO2 appears when the ventilator has a capnography module or when a separate capnograph, such as RICAP, is connected to it.
3. Do you have ventilators for newborns?
Yes. SIRIO BABY 200 is designed for infants up to 3 kg, and FALCO 202 EVO lets you set tidal volumes starting at 2 mL. Giulia and Baby Start by Ginevri are made specifically for neonatology. For the delivery room there is also the Babypuff 1020 manual ventilator.
4. How long does a portable ventilator run on battery?
It depends on the model. According to the manufacturers, SIRIO S2/T runs for 6 to 6.5 hours, FALCO 202 EVO TRANSPORT for up to 8 hours and OXIVENT for up to 10 hours. A stationary ventilator also needs a battery so that ventilation keeps going during a power cut.
5. What is a ventilator made of, and what do you buy for it later?
The core is a control unit with a display and a turbine or pneumatic unit. Valves and sensors sit inside, and gas reaches the patient through a breathing circuit. Over the service life you keep buying circuits and bacterial-viral filters, as well as flow sensors, NIV masks or humidifier chambers. Plan them into the purchase.

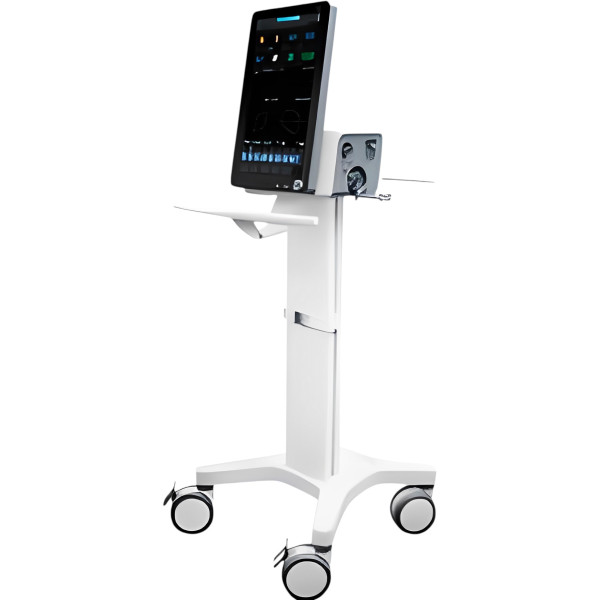
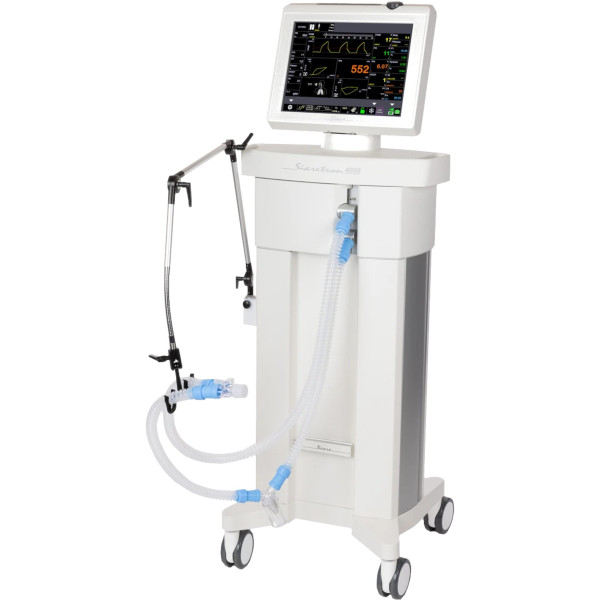 SIAREHigh-Power Lung Ventilator SIARETRON 4000High-Power Lung Ventilator SIARETRON 4000Request priceView details
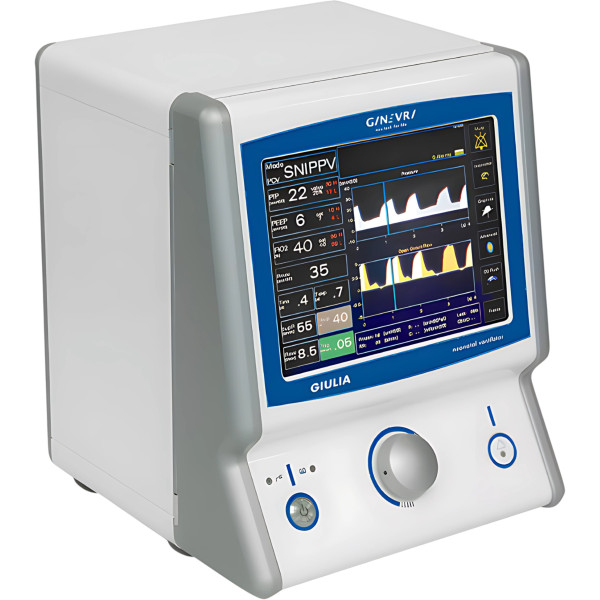 GinevriNeonatal mechanical ventilator GiuliaNeonatal mechanical ventilator GiuliaRequest priceView details
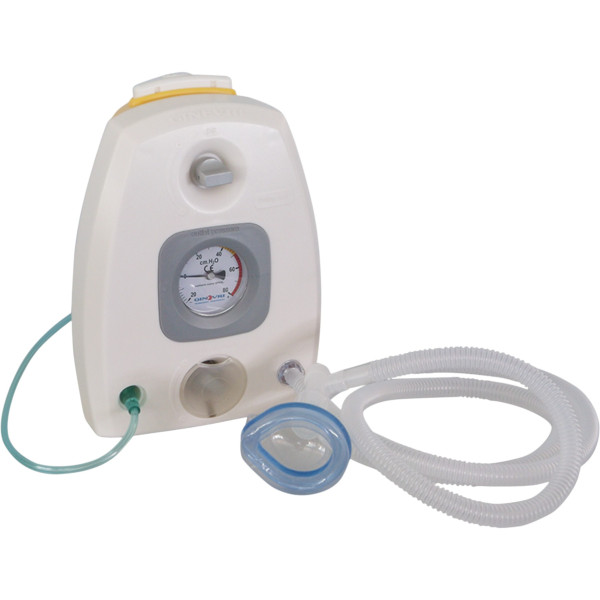 GinevriPneumatic mechanical ventilator Baby StartPneumatic mechanical ventilator Baby StartRequest priceView details
 ChenweiPortable mechanical ventilator CWH-2010Portable mechanical ventilator CWH-2010Request priceView details